Senior living operators are solving for symptoms. Here’s what to fix instead.
Operations, staffing, and financial performance in senior living don’t move independently, but rather as a system. When one is under strain, the other two are likely to follow. And when communities manage them as separate departments with separate budgets and reporting, they end up treating symptoms rather than solving root causes.
That’s one of the core findings in SafelyYou’s 2026 Cost of Senior Care Study. For a typical 100-resident community, unplanned annual costs driven by falls, staff turnover, and resident transitions can climb to between $900,000 and $1.15 million. But, when each measure is viewed independently, nothing material changes and costs continue to rise.
When operations, staffing, and financial performance are viewed under one umbrella, issues that touch all three can be diagnosed more easily and the root cause of the issue can be resolved, saving time, money, and resources.
A view into the cycle.
When issues arise in senior living operations, staffing, or financial performance, there’s a good chance that they will trickle down to affect the other two areas. The clearest way to see how interconnected these areas are is to follow a single pressure point: falls.
Let’s start with staffing shortages. When staffing coverage runs thin, residents wait longer between check-ins, preventive care slips through the cracks, and hazards go unnoticed; all of which can contribute to falls among residents. And when a fall does happen, clinical staff shift into response mode and spend time on documentation, family calls, and care plan updates. The 2026 Cost of Senior Care Study found that clinical staff spend the equivalent of a full workday per week on fall-related tasks like these.
That sustained workload accumulates into burnout, which drives turnover. Replacing a frontline caregiver can cost upwards of $7,160, while replacing a clinical leader costs between $20,450 to $21,660. And those figures only cover recruiting, onboarding, and training. Lost institutional knowledge and the supervision burden on remaining staff don’t appear in that math. And a team that just lost experienced members is now thinner on coverage than it was before.
The financial impact of staff turnover is significant in itself, but the financial impact of the resulting gaps in care–especially in relation to falls– is also worth noting. Fall-related move-outs — which account for 1 in 7 senior living move-outs according to the Cost of Falls Report — trigger an immediate revenue drop and another full sales cycle to backfill the room. Total fall-related costs average $380,000 per community per year when you aggregate staff time, documentation burden, clinical follow-up, and vacancy.

None of that is visible in any single department’s reporting. It’s only visible when you look at the system.
Why silos form in the first place.
The separation between operations, staffing, and finance reflects how most senior living organizations are built. Each department has its own leadership, its own reporting cadence, and its own definition of success. The director of nursing is focused on care quality and incident rates. HR is focused on time-to-fill and retention. Finance is focused on occupancy and margin. Each is doing exactly what it’s supposed to do, and none of those metrics are designed to surface how one department’s pressures are creating costs in another.
That’s why reactive management cultures are created over time. When departments aren’t regularly looking at each other’s numbers in context, problems tend to get addressed after they’ve already generated costs. A staffing shortage may not register as a financial risk until it shows up in turnover expenses or a fall-related move-out. A rise in fall frequency may not register as a staffing issue until burnout is already influencing exits. By the time any of it surfaces in a budget review, the expense has already been absorbed.
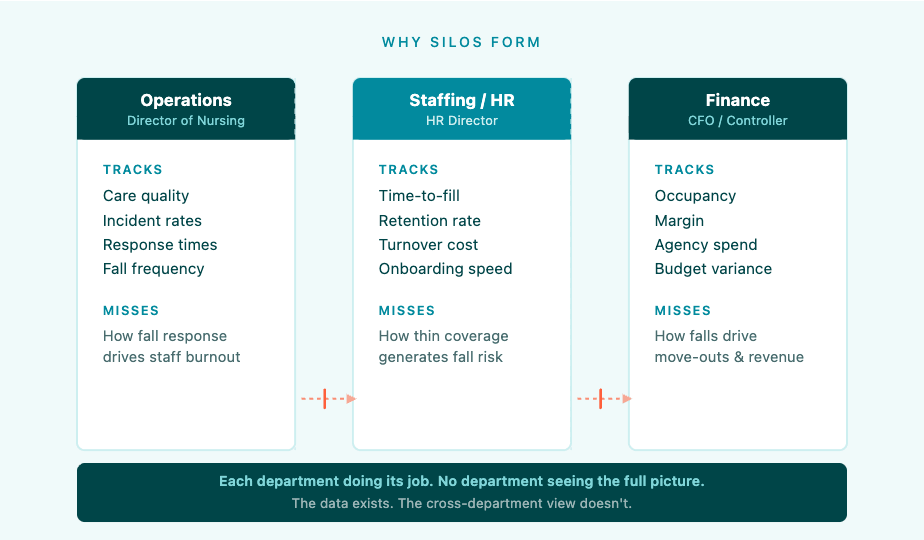
The data exists within the organization. What’s harder to establish is a clear view of how it all fits together. Understanding why the silos form makes it easier to know where to intervene. Here’s what that looks like in practice.
What it looks like to manage them together in practice.
Managing operations, staffing, and finance together in senior living requires a shift in how leadership asks questions. Most communities have the data they need, it’s just organized in a way that keeps the connections invisible. The starting point is changing what you’re looking for. The strategic shift is straightforward to name and genuinely hard to execute: stop asking “how is our staffing?” and start asking “what is our staffing telling us about our operations and our margin?”
Here’s what that looks like at the ground level.
Build a shared visibility cadence
The most common structural barrier to connected management is that clinical, HR, and finance meet separately, report separately, and may not see each other’s numbers in context. A monthly cross-functional review — even a 45-minute meeting with clinical leadership, the HR lead, and whoever owns your P&L — surfaces patterns that siloed reporting can’t.
Reframe prevention spending as margin protection.
The instinct in most senior living ownership conversations is to scrutinize new technology or staffing investments as cost additions. The more accurate frame is to compare them against what reactive management is already costing — costs that are currently buried in three separate budgets and labeled as normal operating expenses. When communities catch acuity changes earlier, SafelyYou internal data shows average resident length of stay extends by 174 days. Fewer fall-related transitions mean fewer unplanned vacancies and less constant backfill pressure on your sales team.
Track leading indicators, not just lagging ones.
Incident counts, turnover rates, and occupancy numbers are all lagging indicators — they tell you what already happened. The communities that break the reactive cycle do it by tracking what predicts those outcomes: care task completion rates, response time patterns, acuity trends, staff hours per resident. When those numbers move, the downstream financial impact is usually still preventable. By the time it shows up in your P&L, it isn’t.
The whole picture.
The senior living communities that manage operations, staffing, and finances as a single system have a clearer view of how challenges connect. And it doesn’t require a new organizational structure. It requires a decision to stop treating connected problems as if they’re separate ones.
In practice, a director of nursing and a finance lead are looking at the same numbers in the same meeting. The budget has a line for what reactive management actually costs, not just what each department spent. Leadership is tracking the metrics that predict problems rather than the ones that confirm them after the fact.
That clarity is what makes the difference — not just in catching problems earlier, but in resolving them at the source instead of absorbing their cost downstream across three department budgets.
The 2026 Cost of Senior Care Study maps the full picture — what communities are spending now, where those costs are actually coming from, and what changes when operations, staffing, and financials are managed as a connected system.
Download the study and see the data for yourself.
Frequently Asked Questions
Why do operations, staffing, and financial performance in senior living tend to decline together even when each department appears to be functioning well?
Because the costs driving all three often share the same origin. When fall frequency rises, clinical staff shift into response mode, which reduces the preventive work that keeps residents safer and staff schedules manageable. That workload builds into burnout, burnout drives turnover, and thinner coverage makes the next fall more likely. Each department registers a problem it can manage on its own. The underlying cycle continues generating the same costs across all three.
Why are falls such a reliable indicator of broader operational health?
Because a fall doesn’t stay in the clinical department. It pulls staff time away from preventive care, contributes to the burnout that drives turnover, triggers a potential move-out, and leaves a vacancy that takes months and meaningful sales effort to fill. When fall frequency is rising, it’s rarely just a clinical signal. It’s usually an early indicator that staffing coverage is strained and that financial pressure is building — often before either shows up in department-level reporting.
What does it actually mean to manage operations, staffing, and financials as a connected system?
In practical terms, it means the right people are looking at the same data at the same time. A monthly cross-functional review that brings clinical leadership, HR, and finance into the same conversation surfaces patterns that siloed reporting never will. It also means building a budget line that captures what reactive management actually costs across departments — not just what each department spent individually. Most communities already have the data they need. The missing piece is a structure that makes the connections between it visible.
How do we make the case to ownership for investing in prevention when the returns aren’t guaranteed?
The most effective frame isn’t about projecting future returns. It’s about quantifying what reactive management is already costing. If your community is absorbing $380,000 in annual fall-related costs spread across three department budgets, that number exists whether or not it has a line item. Presenting it as a single connected cost — alongside turnover expenses and fall-related vacancy loss — shifts the conversation from “should we spend on prevention?” to “is this a better use of dollars we’re already spending?”
Where should a senior living operator start if they want to break the reactive cycle?
The most accessible starting point is changing what gets reviewed together. Before adding new tools or restructuring departments, put clinical, HR, and finance leadership in the same room with each other’s numbers on a regular cadence. Fall frequency next to turnover rates next to vacancy trends tells a different story than any one of those metrics on its own. From there, the root causes become easier to identify — and the interventions become easier to prioritize.